
What is Lp(a), and should you get it tested?
Lp(a) is an inherited cardiovascular risk factor often missed by standard cholesterol tests. Discover how testing can guide a personalised prevention plan.
- Updated
- 5 min read
- By Charmaine Shepherd, IFM Certified Practitioner

Lp(a) is a cholesterol-carrying particle whose level is largely inherited. Raised levels increase cardiovascular risk, even when your standard cholesterol results look reassuring. Knowing your level helps us make prevention more personal: looking at artery health, cholesterol particles, blood sugar, blood pressure and the wider factors influencing your cardiovascular health.
Lp(a), pronounced “L-P-little-a”, is a heart health marker I believe deserves much more attention.
I often meet people who have been told their cholesterol is fine, yet have a strong family history of heart disease. A standard cholesterol panel can leave an important part of that picture unexplored.
From a functional medicine perspective, knowing your inherited risk gives us an opportunity to act earlier and more deliberately.
What is Lp(a)?
Lipoprotein(a) is a particle similar to LDL, with an additional protein called apolipoprotein(a) attached.
It can contribute to plaque formation and inflammatory processes within artery walls. Raised levels are associated with heart attack, ischaemic stroke and calcific narrowing of the aortic valve.
Your level is largely determined by your genes. Someone who eats well, exercises regularly and has a healthy weight can still have high Lp(a).
The useful distinction is between the level you inherit and the overall cardiovascular risk we can work to reduce.
What do Lp(a) levels mean?
HEART UK uses the following categories:
| Lp(a) level | Risk category |
|---|---|
| Below 32 nmol/L | Desirable |
| 32–90 nmol/L | Minor |
| 90–200 nmol/L | Moderate |
| 200–400 nmol/L | High |
| Above 400 nmol/L | Very high |
These describe the risk associated with Lp(a), rather than your total personal risk. That also depends on your other risk factors and whether cardiovascular disease is already present. Risk increases along a continuum rather than suddenly changing at each threshold.
Some laboratories report results in mg/dL. There is no exact universal conversion between mg/dL and nmol/L, so always check the units before comparing results.
In clinic, I interpret Lp(a) alongside your history, other blood markers and, where appropriate, artery imaging.
Who should be tested for Lp(a)?
Testing is particularly useful if you have:
-
a personal or family history of early heart disease or ischaemic stroke
-
a close relative with raised Lp(a)
-
familial hypercholesterolaemia
-
calcific aortic valve narrowing
-
uncertainty about your cardiovascular risk or treatment decisions.
I also favour knowing your Lp(a) as part of a proactive adult heart health assessment. It usually only needs measuring once, and it can reveal inherited risk that a standard cholesterol panel misses.
We do not need to wait for symptoms before discussing prevention.
What can you do if your Lp(a) is high?
A raised result gives us a reason to make your prevention plan more focused. It does not mean a heart attack or stroke is inevitable.
Look beyond total cholesterol. I consider LDL cholesterol, non-HDL cholesterol and, where useful, ApoB, which helps assess the number of atherogenic particles circulating in your blood. With raised Lp(a), managing these additional particles becomes especially important.
Assess metabolic health. Blood pressure, HbA1c, triglycerides, waist measurements and your clinical history help us understand the wider picture. Where appropriate, further assessment can explore insulin resistance and identify practical opportunities to improve metabolic health.
Investigate relevant inflammatory contributors. I consider symptoms, medical history and sometimes markers such as hs-CRP. Gum disease, smoking, excess visceral fat and inflammatory conditions deserve attention. Digestive symptoms may also warrant investigation, without assuming that everyone needs gut testing.
Build a sustainable lifestyle plan. Food quality, adequate fibre, regular movement, strength training, restorative sleep and smoking cessation all matter. The aim is to reduce overall cardiovascular risk, even if your Lp(a) number remains much the same.
Consider artery imaging when it would change the plan. A carotid ultrasound that assesses plaque, or a coronary calcium score, can sometimes add useful information. These tests examine different aspects of artery health. A reassuring scan does not erase the lifetime risk associated with raised Lp(a), and imaging should be selected for a clear clinical reason.
Use medication where it adds protection. Functional medicine can work alongside lipid-lowering treatment. Statins do not lower Lp(a), but reducing LDL can still reduce cardiovascular events. Some people need additional treatment or specialist lipid advice, depending on their overall risk.
Share the finding with your family. Because Lp(a) is inherited, close relatives may benefit from testing and earlier prevention.
This broader, personalised approach is also supported by HEART UK’s emphasis on managing LDL, blood pressure, glucose and lifestyle factors in people with raised Lp(a).
Why isn’t Lp(a) part of a standard cholesterol test?
A standard cholesterol panel usually measures total cholesterol, HDL, triglycerides and an LDL estimate. Lp(a) requires a separate request.
That is why a reassuring cholesterol result can still leave an inherited risk factor undiscovered.
I can arrange Lp(a) testing as part of a heart health assessment and help you understand what the result means in the context of your wider health.
See my heart health guide and Which heart test tells you most?
When to get urgent help
Call 999 for possible heart attack symptoms, including chest pain or pressure, especially with breathlessness, sweating or pain spreading to the arm, jaw, neck or back.
Also call 999 for signs of a stroke, such as sudden face drooping, arm weakness or speech difficulties.
Common questions
Can diet lower Lp(a)?
Diet and exercise usually have little effect on Lp(a) itself because it is largely inherited.
They remain central to your prevention plan. Improving diet, metabolic health, blood pressure and other cholesterol markers can reduce overall risk even when Lp(a) stays raised.
How often should Lp(a) be tested?
For most people, one measurement taken when their health is stable is enough.
A repeat may be useful if the first result was obtained during significant illness, if a medical condition may have affected it, or if a specialist is monitoring treatment. Routine frequent testing is usually less useful than tracking the risk factors we can change.
Do statins lower Lp(a)?
No. Lp(a) may remain unchanged or rise slightly with statin treatment. However, statins can still provide important protection by lowering LDL cholesterol and reducing cardiovascular events.
The treatment decision should reflect your overall risk and clinical history.
Is Lp(a) the same as LDL?
No. Lp(a) resembles an LDL particle but has an additional protein attached, giving it distinct properties and additional cardiovascular risk.
It needs to be measured separately.
Want a fuller picture of your heart health? Book a free discovery call and we’ll discuss your results, family history and the next steps towards a personalised prevention plan.
Sources

Should you have a carotid artery scan if you feel well?
Carotid artery scan, cholesterol test or calcium score: which tells you most?
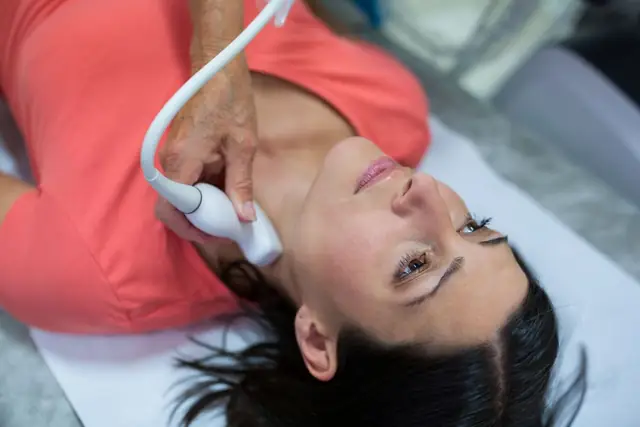
What is a carotid artery scan, and should you have one?
This article is for general information and isn't a substitute for personal medical advice. Please don't start or stop any medication without speaking to your GP or prescriber.